
Courtesy: Prof Nabil Ebraheim, University of Toledo, Ohio, USA
Lumbar Spinal Stenosis: Pathoanatomy, Differential Diagnosis, and Surgical Management
Pathoanatomy & Kinematics
-
Anatomical Definition: Narrowing of the central spinal canal, lateral recesses, or neural foramina.
-
Underlying Etiology: Facet joint arthrosis and hypertrophy, ligamentum flavum buckling and thickening, and degenerative disc bulging.
-
The Flexion Relief Mechanism (Shopping Cart Sign):
-
Trunk flexion increases neuroforaminal cross-sectional area by 12%.
-
Leaning forward over a shopping cart relieves claudicant nerve root ischemia.
-
-
The Extension Penalty:
-
Trunk extension narrows neuroforaminal dimensions by 20%.
-
Extension exacerbates ligamentum flavum buckling and increases canal stenosis.
-
-
Subtype Manifestations:
-
Central Canal Stenosis: Impinges the cauda equina, causing neurogenic pseudoclaudication.
-
Lateral Recess Stenosis: Compresses traversing nerve roots within the subarticular canal.
-
Neural Foraminal Stenosis: Compresses exiting nerve roots beneath the pedicle.
-
Clinical Presentation & Neurological Examination
-
Key Clinical History: History is the single most sensitive tool for identifying spinal stenosis.
-
Neurogenic Claudication: Burning pain, heaviness, weakness, numbness, and cramping across the buttocks, thighs, and calves during ambulation.
-
Neurological Exam Disparity: Physical and neurological examinations are entirely normal in approximately 50% of resting patients.
-
Provocative Postures: Walking upright aggravates discomfort. Sitting or leaning forward promptly alleviates leg symptoms.
Neurogenic vs. Vascular Claudication
-
Both conditions present with walking intolerance and symptom relief upon sitting.
-
Standing Still: Relieves vascular claudication by resting ischemic leg muscles, but fails to relieve neurogenic claudication due to sustained lordosis.
-
Stationary Bicycle Test:
-
Relieves neurogenic claudication because the trunk remains flexed.
-
Aggravates vascular claudication because working calf muscles demand increased arterial flow.
-
-
Pain Progression:
-
Neurogenic pain originates proximally in the back or buttocks and spreads distally down the legs.
-
Vascular pain originates distally in the calf muscles and works proximally.
-
-
Vascular Screening: Peripheral pulses must be examined to evaluate concomitant peripheral vascular disease.
Diagnostic Red Flags & Tandem Stenosis
-
Upper Motor Neuron Signs: Hyperreflexia, clonus, Babinski signs, and spastic gait disturbance cannot be caused by lumbar canal stenosis.
-
Cervical Myelopathy: When low back pain accompanies upper motor neuron signs, obtain a cervical spine MRI to rule out cervical cord compression.
-
Directional Lumbar Pain Differentials:
-
Pain aggravated by extension indicates spinal stenosis, facet arthropathy, or degenerative spondylolisthesis.
-
Pain aggravated by flexion indicates discogenic pathology or acute disc herniation.
-
-
Differential Considerations: Rule out advanced hip osteoarthritis, spinal metastases, and retroperitoneal tumors.
Surgical Indications & Operative Strategy
-
Central Canal Decompression: Open or minimally invasive lumbar laminectomy.
-
Lateral Recess Decompression: Medial facetectomy and undercutting of the superior articular process.
-
Indications for Concomitant Arthrodesis (Fusion):
-
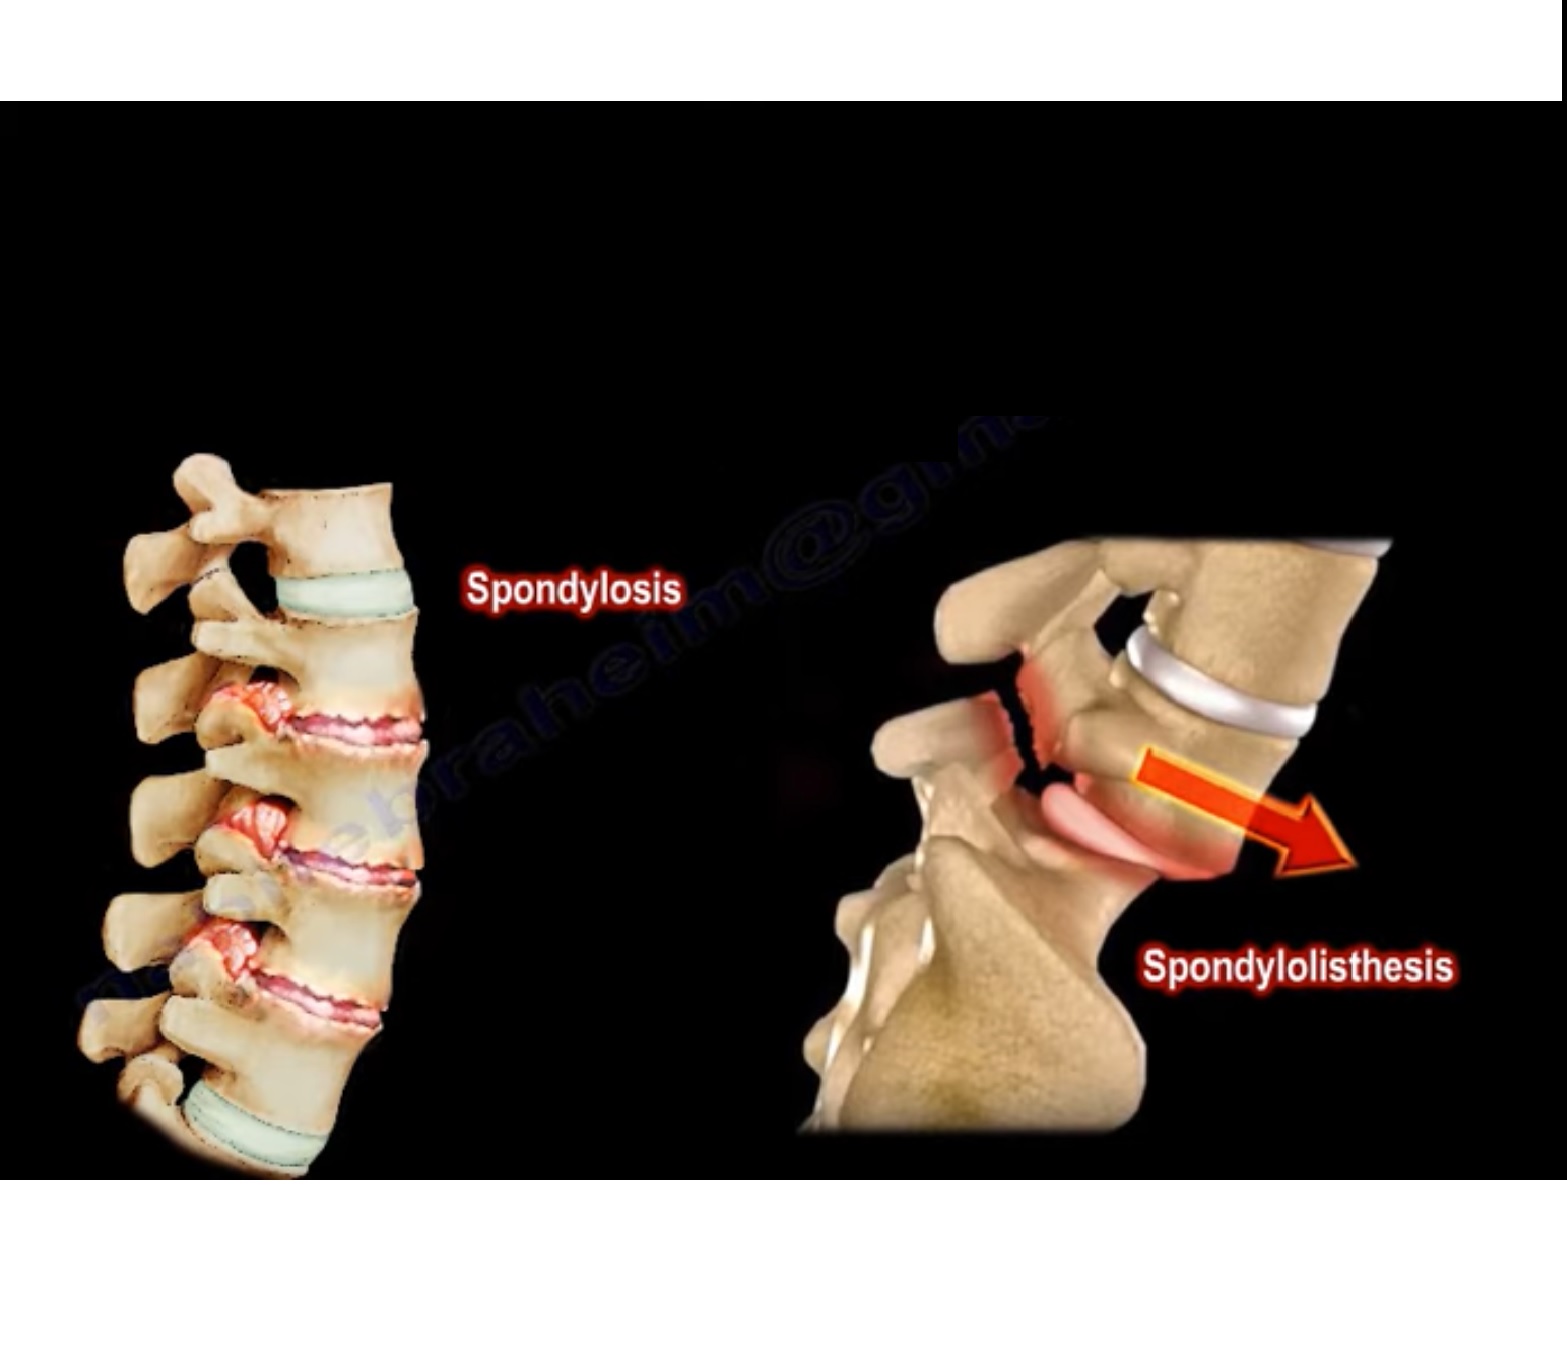
Pre-existing structural instability, such as degenerative spondylolisthesis.
-
Iatrogenic instability caused by resection of greater than 50% of bilateral facet joints (or complete unilateral facetectomy).
-
-
Outcomes at Two Years: Surgical decompression delivers superior functional recovery and pain relief compared to persistent conservative therapy.
-
Pseudarthrosis Risks: Cigarette smoking increases the relative risk of fusion non-union up to 500% (5-fold elevation).
-
Surgical Failure: Recurrent stenosis at adjacent or index levels remains the leading cause of late operative failure.
Leave a Reply